Pain rests at the core of scientific work, from the stressed back in health care to the breast trauma getting here in resuscitation. Yet official training in pain evaluation and multimodal management typically routes behind the need. A certificate program hurting administration can shut that void, aligning useful skills with evidence and administration. The most effective programs surpass procedures. They educate professional judgment, communication under pressure, and application in imperfect real-world settings.
I have actually educated and monitored clinicians through pain administration training across hospitals, social work, and industrial websites. Accreditation and pathways issue. They shape trustworthiness, range of technique, and whether your hard-won skills translate into far better person care. Right here is how I recommend medical professionals to approach the landscape, with detail on accreditation paths, core proficiencies, emergency situation applications, and just how to choose the ideal discomfort management qualification course for your role.
What "approved" actually means
Accreditation is not one point. It is a split idea that covers quality control, alignment with expert requirements, and recognition by employers or regulatory authorities. A certificate training course in pain management may be:
- Professionally approved: Recommended for proceeding professional advancement or proceeding education (CPD/CE) by nursing or physiotherapy bodies, medical universities, or paramedicine councils. Competency-based or unit-aligned: Mapped to specific expertises such as analysis structures, safe opioid stewardship, and procedural analgesia. Recognized for range extension: In some territories, effective conclusion sustains prolonged practice benefits, as an example nurse-initiated analgesia paths or step-by-step sedation credentialing.
These layers are not interchangeable. A glossy badge for CPD hours might aid with yearly enrollment yet does not guarantee practical competence. On the other hand, a strenuous assessment-based program that consists of monitored situations may not automatically draw in CPD points unless the carrier uses. The toughest pain monitoring training programs commonly combine official endorsement with significant assessment of skill.
The PUAEme008 recommendation and why it maintains coming up
Clinicians, especially those working in emergency situation, first response, and commercial health, often see recommendations to puaeme008 offer discomfort monitoring. That code shows up in trade frameworks where devices specify specific skills. In plain terms, puaeme008 provide pain monitoring defines competencies for acknowledging pain, selecting risk-free and reliable interventions, keeping track of reaction, and escalating or referring when required. It versions practice in setups where timely relief is both safety-critical and legitimately bounded by protocols.
If a training provider advertises puaeme008 provide pain monitoring, confirm they evaluate to that system's end results, not simply show around it. Ask about simulation fidelity, circumstance intricacy, and whether the evaluation consists of both pharmacological and non-pharmacological methods. If your company requires puaeme008 for website job, ensure the certificate plainly specifies this unit was attained, not merely "covered."
Core material a reputable pain administration training course should cover
Across careers, you are looking for deepness in these locations:
Pain evaluation. Past numerical scales, clinicians require to distinguish nociceptive, neuropathic, and nociplastic features, and to make use of useful goals. In older adults, cognitive disability and sensory modifications modify discussion. In youngsters, developing tools and caregiver input matter. Acute care depends on fad tracking under evolving conditions.
Pharmacology and security. A major pain management certification program will certainly consist of multimodal pharmacology with realistic person complexity. That means titration of short-acting opioids with clear indications and understood endpoints, non-opioid adjuncts such as NSAIDs, acetaminophen, ketamine in sub-dissociative application, lidocaine patches, and local methods where extent allows. They ought to deal with opioid conversions, kidney and hepatic application, QT risks, serotonin disorder, and drug-drug interactions.
Procedural and local choices. Also if you do not do nerve blocks, recognizing when a fascia iliaca block, hematoma block, or periarticular infiltration boosts results will certainly transform your references and partnership. Physio therapists take advantage of recognizing block timing and rebound patterns to strategy mobilization. Registered nurses in emergency can prepare for analgesic voids as blocks use off.
Non-pharmacological methods. Ice, elevation, splinting, positional strategies, and cognitive strategies can go down pain ratings quickly and reduce opioid usage. Postoperative and trauma settings commonly underestimate these fundamentals, yet they are low risk and highly reliable when done early and consistently.
Documentation and communication. Charting pain assessment, action to treatments, and negative impacts is a safety measure, not an invoicing exercise. Excellent programs instruct concise, defensible notes, individual approval for reversible dangers, and handover structures that maintain analgesia constant across shifts.
Ethics, equity, and prejudice. Researches reveal discomfort undertreatment in certain populations, consisting of those with limited English, compound usage background, and persistent discomfort. Any trustworthy pain monitoring training course ought to help medical professionals recognize prejudice, navigate requests securely, and avoid corrective framing.
Pathways by profession
Different functions require customized pathways and analyses. Discomfort administration training courses for nurses, physio therapists, and others must reflect their lawful extent and daily work.
Nurses. For intense care registered nurses, modules on nurse-initiated analgesia, titration methods, and monitoring for breathing anxiety are necessary. Pain management training for nurses should include rapid assessment in triage, use analgesic ladders, pediatric dosing, and escalation standards. If your service runs nurse-led procedural sedation, seek an accreditation with airway, capnography, and sedation reversal training, plus annual recertification. Nurses in aged care and hospice require additional web content on long-acting opioid rotation, bowel irregularity prophylaxis, and deprescribing.

Physiotherapists. Pain administration programs for physiotherapists need to hang around on graded direct exposure, pacing, main sensitization, and communication that decreases worry and catastrophizing. Severe musculoskeletal discomfort frequently replies to education, very early movement, and adjunctive techniques. The greatest programs integrate discomfort neuroscience education and learning with functional loading progressions and outcome steps, after that link to referral pathways when warnings appear or pharmacologic input is needed.
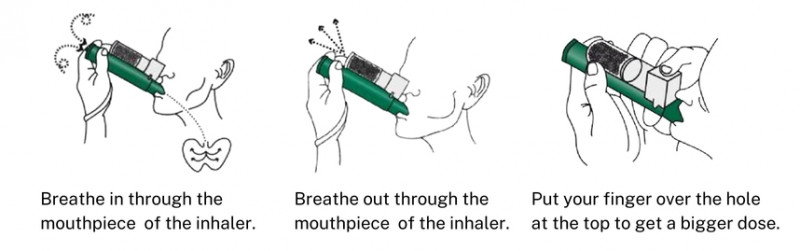
Paramedics and very first responders. Emergency pain administration demands quick, safe, protocol-based choices in constricted atmospheres. Courses aligned with puaeme008 supply discomfort management and comparable units should include intranasal fentanyl or ketamine titration, splinting, shed air conditioning, and pediatric adaptations. Practical scenario work makes the distinction here.
Primary treatment physicians and doctor associates. Outpatient job needs danger assessment for opioid prescribing, pee drug screening protocols where ideal, multimodal planning, and tapering strategies. Time performance matters, so programs that give templated treatment strategies and quick evaluation frameworks will certainly see more use in practice.
Allied health and wellness throughout area and rehab. Chronic pain web content need to move past lectures into case-based experiment measurable functional objectives. Interdisciplinary exercises teach how to develop a common plan without puzzling the individual with blended messages.
What evaluation need to look like
Exams are not enough. Skill hurting administration shows at the bedside. When I assess a discomfort management certification, I try to find multiple evaluation settings: pre-course reading with tests to standardize understanding; observed substitute experiment respiratory tract devices, mixture pumps, or ultrasound designs if blocks are in scope; situation write-ups showing rationale, danger analysis, and follow-up; and live feedback with removal if a candidate battles with dosing or communication. Programs that sign off on competence after a single-choice test usually leave clinicians underprepared.
Short courses in pain administration versus prolonged tracks
You will find two broad kinds of offer: short training courses in pain administration, frequently 1 to 3 days with combined on-line modules; and longitudinal programs running 6 to 16 weeks with workplace jobs or monitored cases.
Short training courses function well for focused objectives: updating emergency situation discomfort management procedures, discovering sub-dissociative ketamine usage, or aligning a ward on documents standards. They are less efficient for mindset shifts required in chronic pain or complex opioid management, where reflection and supervised technique matter. Prolonged programs validate the time by installing method adjustments. The trade-off is schedule and price. If budget plan limits you to a short course, choose one that consists of circumstance work and follow-up mentoring sessions.
The special case of emergency discomfort management
Pain in emergency situations establishes a tone for the whole client journey. If we get analgesia right early, we minimize ecstasy, enhance procedural success, and build count on. A solid emergency situation discomfort https://telegra.ph/Emergency-Situation-Pain-Administration-Best-Practices-from-PUAEME008-12-14 component must emphasize rapid screening for warnings, non-opioid first-line options when appropriate, and very early use regional strategies in hip fractures, rib trauma, or forearm cracks where experienced personnel are available.
Edge situations matter. The person with suspected head injury and hypotension. The older adult with rib cracks and COPD on home oxygen. The child with a lower arm defect in extreme distress. Protocols overview, but the clinician's calibration figures out risk-free titration. Training should include micro-dosing strategies, for instance fentanyl 0.5 to 1 mcg/kg intranasal with review every 5 minutes, or ketamine 0.1 to 0.3 mg/kg IV for analgesia with clear stop policies. The training course ought to also show when to pivot to non-pharmacological actions like splinting before rising medications.
Integrating qualification into your practice
Certification only matters if it transforms your service. When teams return from a pain administration accreditation program, I inquire to pick three execution tasks for the next month. Instances consist of embracing a standardized pain analysis tool throughout triage and inpatient wards, establishing a nurse-initiated analgesia procedure with requirements and guardrails, and constructing a simple order set that packages acetaminophen, NSAIDs where secure, and topical agents before opioids for common conditions. The following quarter, we examine two signs: time to very first analgesia and portion of individuals obtaining multimodal therapy. Tiny, repeated renovations defeated a rack of certificates.
Selecting a supplier: functional vetting
You do not need a thousand-line spreadsheet to vet a program. Four questions normally reveal the truth.
- Who teaches it, and what is their professional money? A program taught by individuals that still take calls or work shifts will certainly really feel different. They show compromises, not simply pathways. How is skills assessed? Seek straight monitoring, case-based conversations, and comments loopholes. If evaluation is just a multiple-choice quiz, be cautious. What acknowledgment does it lug? CPD/CE credit scores aid. Positioning with competencies or units such as puaeme008 offer pain management manages transportability throughout employers. Ask whether your hospital or solution approves the certification for credentialing. What support exists after the training course? Accessibility to sources, instance consults, and updates over the next year increases the value.
Legal and moral boundaries
Pain management intersects with controlled substances, consent, and documentation demands. Training needs to spell out your local legal limits. Nurse-initiated opioid procedures, for example, must be accepted, with dosing varieties, review periods, and rise requirements. Physiotherapists generally can not prescribe opioids, but they bear a task to determine uncontrolled discomfort and advocate or refer. The program must coach clinicians to document rationale in addition to numeric scores: function, goals, negative impacts, and individual understanding.
Equally vital is opioid stewardship. A pain management program that disregards reliance danger, aberrant actions, and non-pharmacological alternatives is insufficient. Yet stewardship should not change right into predisposition or undertreatment. Great training frameworks take the chance of mitigation as well balanced care, not gatekeeping.
Digital and mixed knowing that actually works
Online modules can show core pharmacology and theory efficiently. Where combined discovering sparkles is in the practical layers. Short video clip demos of discomfort evaluation in the nonverbal grownup, splinting techniques that stop pressure factors, and caregiver training for pediatric burns frequently provide a lot more retention than message. Live virtual instance conversations, with participants presenting anonymized instances, assistance bridge classroom and facility. Be careful programs that stuff too much into easy video. If you finish an eight-hour component with even more questions than responses, the layout most likely relied on discussion over practice.
The certification and your career
A discomfort monitoring certificate signals competence and intent. For nurses, it can sustain development into clinical teacher duties, sharp pain solutions, or triage leadership. For physiotherapists, it reinforces profiles in musculoskeletal, perioperative, and relentless discomfort services, and enhances collaboration with clinical groups. For paramedics and very first -responders, it opens paths to innovative technique or commercial duties where pain protocols need to be implemented without a safeguard nearby.
That claimed, the certification is a beginning point. The medical professionals that absolutely change outcomes use the training to discuss much better procedures, adopt lists that reduce variance, and educate peers. Keep a straightforward profile: situations where you executed multimodal plans, addressed complex analgesia in kidney disability, or made use of non-pharmacological techniques to avoid rise. Those stories lug weight with credentialing committees and working with panels.
A brief comparison of course types and that they suit
Programs differ commonly. Three archetypes appear often.
Hospital-endorsed acute pain training courses. Commonly 1 to 2 days, these training courses teach assessment, opioid titration, and monitoring, with emphasis on ward process. Solid option for nurses and jr medical professionals. They tend to use CPD and prompt work environment relevance.
Emergency discomfort administration intensives. Often scenario-heavy, they focus on rapid choices, pediatric application, intranasal choices, and injury analgesia, occasionally with regional blocks. Good for ED team, paramedics, and immediate care. Try to find a program that includes simulation and respiratory tract training.
Interdisciplinary chronic and relentless pain certifications. Longer duration, case-driven, with discomfort neuroscience, behavioral methods, medication management, and team-based preparation. Best for physiotherapists, General practitioners, psycho therapists, and pharmacists working in integrated treatment. Implementation coaching is a differentiator here.
How to obtain one of the most value from your enrollment
A course alone will certainly not reset routines. Strategy your application ahead of time. Select 2 patient populaces in your method that fight with pain management. Typical choices include older adults with hip fractures and individuals with rib cracks and COPD. As you discover, gather devices that fit those cases, for example a fascia iliaca block recommendation formula or a rib crack bundle with reward spirometry, local anesthesia reference criteria, and non-opioid anchors. Set up a short in-service with your team the week after the program, concentrating on those two populations. Then measure one variable for a month, such as time to initial dosage or percentage obtaining multimodal therapy. These tiny cycles transform training into outcomes.
Where puaeme008-linked training rests within broader curricula
Units such as puaeme008 offer discomfort management typically live within emergency care, public safety and security, or industrial wellness frameworks. They are not suggested to change expert acute pain services or chronic pain fellowships. Instead, they elevate the floor for risk-free, consistent pain alleviation in setups where timely action matters. If your service works in remote or resource-limited atmospheres, this unit-aligned training comes to be a safety standard. Couple it with periodic drills, medicine checks, and set audits. The objective is capability that survives the shift from class to roadside or manufacturing facility floor.
Cost, time, and return on investment
Prices differ widely. Brief accredited courses for people typically vary from a modest fee to a number of hundred bucks, depending upon simulation sources and faculty. Team-based onsite training prices a lot more but can systematize method throughout an unit in a single day. The return appears in fewer damaging events, much shorter sizes of stay for common injuries, and much better client satisfaction ratings. From a clinician's perspective, the return is job utilize and more secure decision-making. If your company uses research support, construct a basic service situation: current discomfort metrics, anticipated modifications, and how the program lines up with institutional goals.
Common challenges and exactly how to avoid them
The most regular challenge is mistaking CPD hours for clinically meaningful training. Hours matter much less than web content and analysis. An additional is overconfidence after pharmacology components without hands-on monitored titration or simulation. Opioid-naive individuals with rest apnea, older grownups with kidney impairment, and polypharmacy present truths that require technique, not simply theory. Ultimately, groups occasionally apply new methods without auditing results. Without feedback, difference slips back in.
Bringing it together
Pain administration is both science and craft. A well-chosen discomfort monitoring certification program hones both, particularly when it consists of assessment effectiveness, emergency situation scenarios, and execution assistance. Whether you are exploring discomfort administration courses for nurses, discomfort management programs for physio therapists, or a general discomfort management certification targeted at interdisciplinary teams, support your choice in certification clarity, ability analysis, and post-course combination. If your setting ask for emergency readiness, a program straightened with puaeme008 provide pain management can furnish you to act decisively and safely.
Choose with intent. Ask difficult inquiries of service providers. Then bring the finding out back to your unit with resources for puaeme008 pain management a strategy that fits your clients, your protocols, and your restrictions. The outcomes show up where it counts, in relieved faces, smoother treatments, and fewer dilemmas that could have been avoided with timely, thoughtful care.
